Reading Between the Lab Results: What Every Blood Test During Prednisone Therapy Is Actually Telling Your Doctor

More Than a Formality
If you have been on prednisone for more than a few weeks, you have likely noticed that your physician orders blood work with a regularity that can feel disproportionate to how you are feeling. You may have even wondered whether all those lab orders are truly necessary or simply a precautionary habit. The answer, in almost every case, is that they are necessary—and each test is designed to detect a specific category of harm that prednisone is known to cause before that harm becomes clinically apparent.
Understanding what your doctor is looking for, and why, transforms these appointments from mysterious obligations into meaningful checkpoints in your care.
Blood Glucose: The Steroid Diabetes Problem
Among the first concerns a physician has when initiating prednisone therapy is its effect on blood sugar. Corticosteroids stimulate the liver to release stored glucose and reduce the sensitivity of cells to insulin—a combination that can push fasting glucose into prediabetic or diabetic ranges even in patients who had no prior metabolic concerns.
Your lab report will show a fasting glucose value, typically measured in milligrams per deciliter (mg/dL). A reading below 100 mg/dL is generally considered normal; values between 100 and 125 suggest prediabetes; 126 or above on two separate occasions meets the clinical threshold for diabetes. Your physician may also order a hemoglobin A1c (HbA1c) test, which reflects average blood sugar over the preceding two to three months and provides a longer-term picture than a single fasting measurement.
Patients already managing type 2 diabetes require particularly close monitoring, as prednisone can cause their existing medication regimen to become inadequate almost overnight. Even patients with no prior diagnosis may need temporary glucose-lowering intervention during a long course of corticosteroid therapy.
Potassium and Electrolytes: The Quiet Imbalance
Prednisone influences the kidneys' handling of electrolytes, particularly potassium and sodium. It promotes sodium retention—which contributes to fluid retention and elevated blood pressure—while simultaneously increasing potassium excretion. Low potassium, or hypokalemia, may present as muscle weakness, fatigue, or heart rhythm irregularities, though in mild cases it produces no noticeable symptoms at all.
A basic metabolic panel (BMP) or comprehensive metabolic panel (CMP) will include a potassium value; the normal range is roughly 3.5 to 5.0 millimoles per liter (mmol/L). Sodium, bicarbonate, and kidney function markers such as creatinine and blood urea nitrogen (BUN) are typically included in the same panel, giving your physician a broad view of how your kidneys and fluid balance are responding to treatment.
Patients taking diuretics—a common medication for blood pressure management—face compounded risk, as many diuretics also lower potassium. Your care team will weigh these interactions carefully when interpreting your results.
Lipid Panel: The Cardiovascular Dimension
Long-term or high-dose prednisone use is associated with dyslipidemia—an unfavorable shift in cholesterol and triglyceride levels that increases cardiovascular risk. Specifically, corticosteroids tend to raise LDL (low-density lipoprotein, often called "bad" cholesterol) and triglycerides while potentially reducing HDL (high-density lipoprotein, or "good" cholesterol).
A standard lipid panel measures total cholesterol, LDL, HDL, and triglycerides. Your physician will compare these values against your baseline and against established cardiovascular risk thresholds. Patients on extended prednisone courses who develop worsening lipid profiles may be candidates for dietary modification, statin therapy, or both—a decision that requires the context your lab results provide.
Bone Density Imaging: The Silent Erosion Monitor
Unlike the blood tests described above, bone health monitoring during prednisone therapy typically involves imaging rather than laboratory analysis. A dual-energy X-ray absorptiometry (DEXA) scan measures bone mineral density at the hip and lumbar spine, producing a T-score that compares your density to that of a healthy young adult reference population.
T-scores between -1.0 and -2.5 indicate osteopenia (reduced bone density); scores below -2.5 meet criteria for osteoporosis. Because prednisone accelerates bone resorption by suppressing osteoblast activity and reducing calcium absorption from the gut, the American College of Rheumatology recommends baseline DEXA scanning for most patients who are expected to take prednisone at doses of 5 mg or more daily for three months or longer, with follow-up scans typically every one to two years.
Calcium and vitamin D supplementation are frequently prescribed alongside prednisone for this reason, and bisphosphonate medications may be added for patients whose DEXA results suggest significant bone loss risk.
Complete Blood Count: Watching the Immune Landscape
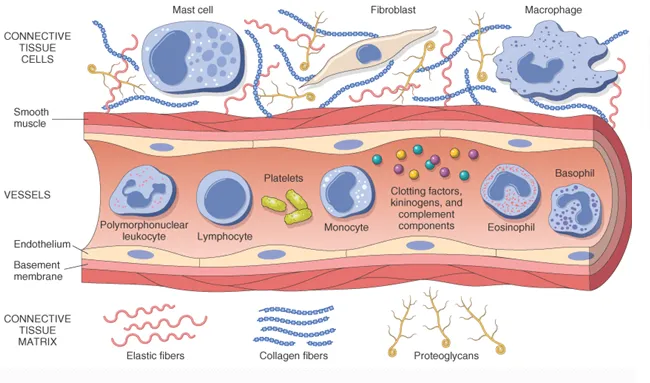
A complete blood count (CBC) measures the various cellular components of blood, including red blood cells, white blood cells (and their subtypes), and platelets. Prednisone's immunosuppressive effects are directly visible in the CBC: the medication typically elevates total white blood cell counts, particularly neutrophils, while reducing lymphocytes—a pattern sometimes called a "stress leukogram."
This shift matters clinically because it can obscure the body's normal response to infection. An elevated white count that would ordinarily signal a developing infection may instead reflect prednisone's pharmacological effect, making clinical interpretation more nuanced. Physicians use the CBC in conjunction with symptoms and other markers to distinguish drug effect from active illness.
Making Your Appointments Count
Armed with this understanding, your next laboratory visit need not feel like a passive exercise. Ask your physician or nurse to walk you through any values that have shifted since your last draw. Request a copy of your results through your patient portal—most major health systems in the United States offer this through platforms such as MyChart—and review the reference ranges provided alongside your numbers.
If a value falls outside the normal range, ask specifically what that means for your current prednisone dose and whether any adjustment to your regimen, diet, or supplementation is warranted. Informed engagement with your lab results is not second-guessing your physician; it is the kind of collaborative participation that supports better long-term outcomes.
At AprednisonLine, we believe that patients who understand their monitoring are patients who stay safer throughout the course of their treatment.